
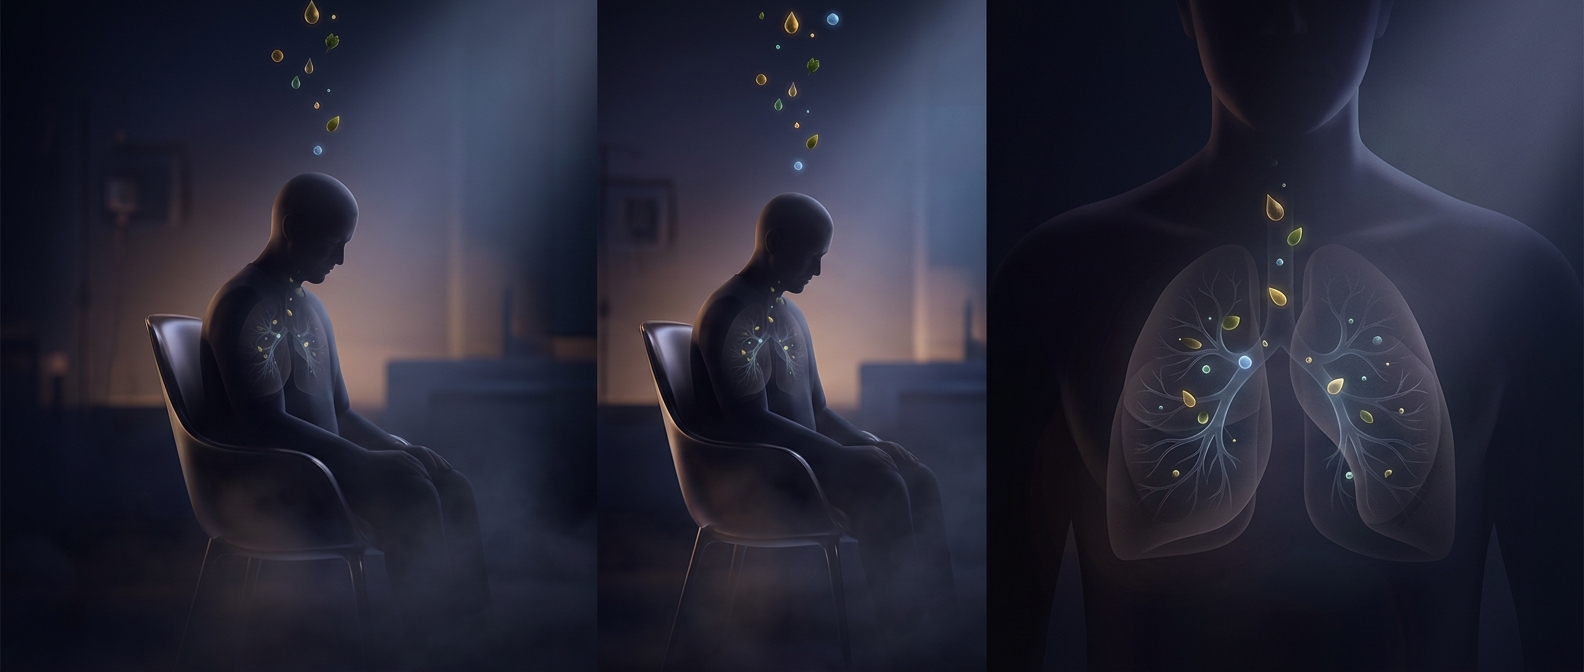
How a stroke can disrupt swallowing
Swallowing is a tightly timed handoff: the tongue moves food toward the throat, while muscles briefly close off the airway so food and liquid travel into the esophagus, the tube leading to the stomach. A stroke can damage the brain networks that coordinate this sequence or carry sensation back from the throat. The result may be dysphagia, the medical term for difficulty swallowing.
If material reaches the airway, coughing is one way the body tries to clear it. But when a stroke also dulls the sensation that something has gone astray, food or liquid may enter the airway without triggering that response. This is called silent aspiration. It can happen with saliva as well as with a meal, so the absence of an obvious choking episode does not guarantee that swallowing is safe.
Why an unnoticed swallow can matter
Material that enters the airway can travel down into the lungs. Repeated aspiration may irritate lung tissue or introduce germs from the mouth, raising the risk of pneumonia. Because the person may not cough, the problem can be harder to recognize from ordinary mealtime behavior alone.
That is why swallowing is assessed after a stroke rather than judged only by whether someone can eat without choking. Clinicians may observe a person swallowing and, when needed, use tests that show how food and liquid move through the throat. The findings help determine what textures, strategies, or other support are appropriate. The key consequence is practical: a quiet meal is not always evidence that the airway is being protected.





